All published articles of this journal are available on ScienceDirect.

Managing Radiation-induced Xerostomia in Head and Neck Cancer: A 2020–2025 Systematic Review
 iD
Hamad Mohammad Aljubair1
iD
Yara Ibrahim Alromaih1
iD
Nada Ayed Alayed1
Authors Info & Affiliations
Abstract
Background
Radiotherapy (RT) is a cornerstone of head and neck cancer (HNC) treatment, but radiation-induced xerostomia (RIX) remains a common complication affecting oral function and quality of life. This review evaluated evidence from 2020–2025 on preventive and therapeutic interventions for RIX.
Materials and Methods
A PRISMA 2020 systematic review searched PubMed, Scopus, and Web of Science for English-language studies published from 2020–2025 evaluating RIX interventions in adults with HNC. RCTs and systematic reviews/meta-analyses reporting salivary flow or validated xerostomia outcomes were included. Of 670 records identified, 220 duplicates were removed, 100 full texts were assessed, and 35 studies were included.
Results
Thirty-five studies were included. IMRT and IMPT consistently improved salivary-gland preservation compared with conventional RT but did not eliminate RIX. Pilocarpine, cevimeline, and amifostine remained the principal pharmacological interventions, although adverse effects may limit adherence in some patients. Photobiomodulation, electrical nerve stimulation, and acupuncture showed potential benefits as adjunctive therapies, although the strength and consistency of evidence varied. Submandibular gland transfer and regenerative approaches, including mesenchymal stem cell therapy, have demonstrated preliminary safety and potential efficacy, but the available evidence remains insufficient to support routine clinical recommendations.
Discussion
Evidence most strongly supports salivary gland-sparing radiotherapy, particularly IMRT and IMPT. Pharmacological and supportive therapies may provide additional symptomatic benefit, while evidence for non-pharmacological and regenerative interventions remains limited.
Conclusion
Current evidence supports an individualized, multimodal approach combining salivary gland-sparing radiotherapy, pharmacotherapy, and supportive interventions. Larger, well-designed trials with standardized outcomes are needed to establish the long-term effectiveness of emerging therapies.
1. INTRODUCTION
Radiation-induced xerostomia (RIX) is a common and debilitating complication in patients undergoing radiotherapy (RT) for head and neck cancer (HNC) [1, 2]. Approximately 60–90% of patients with HNC experience some degree of xerostomia, which can interfere with speaking, mastication, tasting, and swallowing. These disruptions commonly lead to nutritional deficiencies, an increased risk of dental decay and oral infections, and a notable reduction in overall quality of life [2, 3]. Salivary glands, particularly the parotid glands, are highly sensitive to radiation. Conventional RT commonly causes permanent damage to salivary glands due to insufficient protection of essential structures [4]. While glandular recovery may occur after treatment, persistent xerostomia remains a common concern in many patients treated for HNC. Multiple approaches have been studied to support the prevention and management of xerostomia [3-7]. Advances in RT, including intensity-modulated RT (IMRT) and proton beam therapy (PBT), have enhanced treatment precision by targeting tumors and reducing exposure to nearby salivary glands [5, 6]. These improvements have reduced the frequency and severity of xerostomia. However, xerostomia continues to affect some patients, particularly those receiving high-dose RT or with tumors close to the salivary structures [8, 9]. Various preventive and therapeutic strategies have been developed to address this issue. Pharmacological agents, such as pilocarpine and amifostine, aim to support remaining salivary function or protect glands from radiation-induced injury [10-17]. Artificial saliva substitutes and moisturizers provide palliative relief for patients with xerostomia [18]. More recently, non-pharmacological approaches, including photobiomodulation therapy (PBMT), acupuncture, hyperbaric oxygen therapy (HBOT), electrical nerve stimulation (ENS), and intraoral stents, have shown potential in preserving salivary gland function and enhancing comfort [19]. Moreover, surgical techniques such as pre-RT salivary gland transfer have been explored as preventive options in selected cases [6, 7]. A 2023 review by Nathan et al. highlighted the complex causes of xerostomia in patients treated for HNC and emphasized the importance of a multidisciplinary approach. This includes novel RT planning, systemic therapies, and supportive interventions to improve long-term salivary function and overall well-being [3]. Despite advances in RT techniques, xerostomia remains a major concern for patient survival. In this systematic review, this study aimed to summarize the available literature on the prevention and management of RIX, with a focus on recent publications from 2020 to 2025. By integrating findings from multiple disciplines, this review offers clinicians an updated, evidence-based guide to current strategies and emerging research.
Previous reviews of radiation-induced xerostomia have generally focused on individual management approaches, such as salivary gland-sparing radiotherapy, pharmacologic interventions, or selected supportive therapies. Although these studies have provided important evidence regarding the effectiveness of specific modalities, the literature remains fragmented across preventive, pharmacological, non-pharmacological, surgical, and regenerative strategies. In addition, emerging interventions have not consistently been considered alongside established approaches, limiting direct appraisal of the overall therapeutic landscape and the development of integrated management recommendations. To our knowledge, the present systematic review provides one of the most comprehensive syntheses of evidence published between 2020 and 2025 on the prevention and management of radiation-induced xerostomia. It evaluates five major therapeutic domains within a single PRISMA 2020 framework: advanced radiotherapy techniques, including IMRT and IMPT; pharmacologic therapies, including pilocarpine, cevimeline, and amifostine; non-pharmacological and supportive interventions, including photobiomodulation, electrical nerve stimulation, acupuncture, hyperbaric oxygen therapy, and intraoral stents; and surgical and regenerative approaches, including submandibular gland transfer and mesenchymal stem cell-based therapies. By comparatively synthesizing evidence across these modalities, this review aims to support clinical decision-making, identify current evidence gaps, and highlight priorities for future clinical trials and guideline development. The remainder of the manuscript is organized as follows. Section 2 describes the Materials and Methods, including the search strategy, eligibility criteria, study selection process, and risk-of-bias assessment. Section 3 presents the Results, including findings related to radiotherapy modalities, supportive products, pharmacologic agents, non-pharmacological interventions, and surgical and regenerative approaches. The findings are subsequently interpreted in their clinical context in the Discussion, followed by the Conclusion, which summarizes the principal findings and outlines priorities for future research.
2. MATERIALS AND METHODS
2.1. Question Formulation and Location of the Studies
This literature review followed a structured and transparent approach aligned with the 2020 Preferred Reporting Items for Systematic Reviews (PRISMA) guidelines. A comprehensive electronic database search was performed using PubMed, Scopus, and Web of Science to identify studies evaluating preventive and therapeutic interventions for radiation-induced xerostomia in patients with head and neck cancer. Peer-reviewed articles published between January 2020 and December 2025 were included. The search strategy combined controlled vocabulary and free-text terms, and focused on RIX and its management in patients treated for HNC. The search strategy used various combinations of terms with Boolean operators (“AND,” “OR”): “xerostomia,” “radiation-induced xerostomia,” “head and neck cancer,” “IMRT,” “proton beam therapy” or “PMT,” “photobiomodulation,” “pilocarpine,” “cevimeline,” “amifostine,” “artificial saliva,” “electrical nerve stimulation,” “hyperbaric oxygen,” “intraoral stent,” and “salivary gland transfer.” The filters limited the results to English-language publications. Duplicate records were removed using EndNote reference management software. Eligible studies met the following inclusion criteria: they focused on RIX in patients treated for HNC; included clinical trials, systematic reviews, meta-analyses, or high-quality narrative reviews; and were published in English in high-impact journals related to oncology, oral medicine, RT, or supportive care. Studies were excluded if they did not directly address RIX or its management; involved non-HNC populations or animal models; focused only on tumor control, dosimetry, or toxicity without xerostomia outcomes; lacked sufficient data, such as quantitative results or complete intervention details; were not peer-reviewed or of low methodological quality; or were published in languages other than English (Table 1).
| Database | Field Tags | Filters/Limits |
|---|---|---|
| PubMed/MEDLINE | MeSH terms; Title/Abstract [tiab] | English language; January 2020–December 2025 |
| Scopus | Title, Abstract, Keywords | English language; 2020–2025 |
| Web of Science Core Collection | Topic (Title, Abstract, Author Keywords, Keywords Plus) | English language; 2020–2025 |
2.2. Critical Evaluation and Data Collection
The database search yielded 670 records: 220 from PubMed, 170 from Web of Science, and 280 from Scopus. After removing 220 duplicates, 450 unique records were retained for title and abstract screening. Of these, 350 were excluded because of irrelevance or failure to meet the inclusion criteria. A total of 100 full-text articles were evaluated for eligibility. Of these, 65 were excluded because of insufficient data (n = 17), unrelated outcomes (n = 20), or irrelevant interventions (n = 28). Ultimately, 35 studies met all the inclusion criteria and were included in the final review. The PRISMA flow diagram (Fig. 1) outlines the full selection process. The extracted data included authorship, publication year, study design, primary findings, and journal sources. Each article was reviewed in full and classified into one of five thematic categories: preventive strategies, artificial saliva substitutes, pharmacological interventions, non-pharmacological approaches, and surgical interventions. Summary tables (Tables 1–9) for each category present the study characteristics and key findings from articles published between 2020 and 2025.
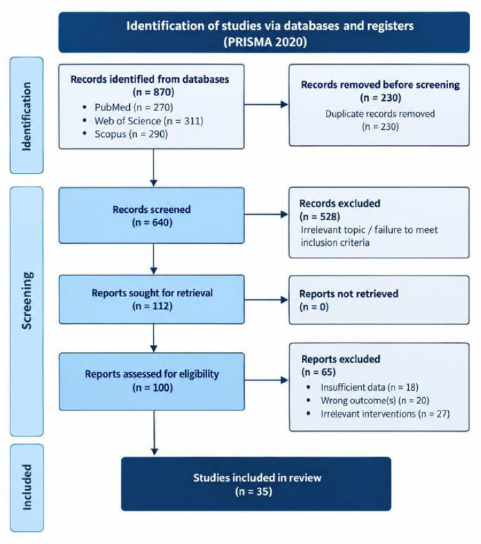
Systematic reviews (PRISMA) 2020 flow diagram of the literature search and study selection.
| S. No. | First Author | Full Title | Year, Citation | Findings |
|---|---|---|---|---|
| 1. | Cao | Intensity-Modulated Proton Therapy for Oropharyngeal Cancer Reduces Rates of Late Xerostomia | 2021, 20 |
Intensity-modulated proton therapy (IMPT) is associated with less late xerostomia compared with IMRT in patients receiving treatment for oropharyngeal cancer (OPC). Oral cavity dosimetric variables are associated with the occurrence of late xerostomia. |
| 2. | De Felice | Xerostomia and Clinical Outcomes in Definitive Intensity Modulated Radiotherapy (IMRT) Versus Three-dimensional Conformal Radiotherapy (3D-CRT) for Head and Neck Squamous Cell Carcinoma: A Meta-Analysis | 2020, 21 |
IMRT reduces grade ≥ 2 acute and late xerostomia compared with three-dimensional conformal radiotherapy (3D-CRT) and shows no notable improvement in overall survival or loco-regional control. |
| 3. | Gerlach | Radiation-induced oral side effects in head and neck cancer: a scoping review and interdisciplinary recommendations | 2026, 22 |
A mean parotid dose threshold below 25 Gy is required for meaningful functional recovery. Exceeding this threshold results in markedly reduced salivary flow with little or no long-term recovery. IMRT offers substantial salivary gland-sparing potential. |
| 4 . |
Yahya | Quality of Life and Patient-Reported Outcomes Following Proton Therapy for Oropharyngeal Carcinoma: A Systematic Review | 2023, 23 |
IMPT shows improved patient-reported outcomes for xerostomia compared with IMRT, particularly in the physical and personal domains. |
| 5. | Youssef | Toxicity Profiles and Survival Outcomes Among Patients With Nonmetastatic Oropharyngeal Carcinoma Treated With Intensity-Modulated Proton Therapy vs Intensity-Modulated Radiation Therapy | 2022, 24 |
IMPT is associated with lower rates of xerostomia and improved patient-reported outcomes compared with IMRT, and survival outcomes remain comparable. |
| S. No. | First Author | Full Title | Year, Citation | Findings |
|---|---|---|---|---|
| 6. | Marimuthu | Saliva Substitute Mouthwash in Nasopharyngeal Cancer Survivors With Xerostomia: A Randomized Controlled Trial | 2021, 26 |
Immunologically active saliva substitutes notably improve patient-reported xerostomia scores and unstimulated salivary flow compared with placebo. |
| 7. | Nuchit | Alleviation of Dry Mouth by Saliva Substitutes Improved Swallowing Ability and Clinical Nutritional Status of Post-Radiotherapy Head And Neck Cancer Patients: A Randomized Controlled Trial | 2020, 27 |
Continuous use of saliva substitutes improves symptomatic xerostomia, swallowing ability, and nutritional status in patients who have completed radiotherapy (RT) for head and neck cancer (HNC). |
| 8. | Piboonratanakit | Trehalose Versus Carboxymethylcellulose Oral Spray for Relieving Radiation-Induced Xerostomia in Head And Neck Cancer Patients: A Randomized Controlled Trial | 2023, 28 |
Trehalose spray improves salivary pH and unstimulated salivary flow rate and shows efficacy comparable to that of carboxymethylcellulose (CMC) spray in enhancing xerostomia-related quality of life. |
| 9. | Lanzetti | Management of Oral Hygiene in Head-Neck Cancer Patients Undergoing Oncological Surgery and Radiotherapy: A Systematic Review | 2023, 29 |
Edible saliva gels and oral moisturizing jellies reduce Candida colonization and enhance saliva properties in patients who have completed RT. Integrated supportive programs improve symptomatic xerostomia and increase unstimulated saliva flow in patients who have completed RT for HNC. |
| 10. | Rupe | Sodium-Hyaluronate Mouthwash on Radiotherapy-Induced Xerostomia: A Randomised Clinical Trial | 2023, 30 |
Sodium hyaluronate mouthwash significantly improves xerostomia symptoms and quality of life without adverse effects. |
| 11. | Porangaba | Randomized Double-Blind Placebo-Controlled Study of Salivary Substitute With Enzymatic System for Xerostomia in Patients Irradiated in Head and Neck Region | 2024, 31 |
Salivary substitutes with enzymatic systems show some improvements in symptomatic xerostomia, but differences compared with placebo do not reach statistical significance. |
| S. No. | First Author | Full Title | Year, Citation | Findings |
|---|---|---|---|---|
| 12. | Watanapokasin | As-Needed Pilocarpine for Radiation-Induced Xerostomia in Head and Neck Cancer Patients | 2024, 17 |
As-needed pilocarpine effectively relieves symptomatic xerostomia with fewer adverse effects and reduces treatment costs compared with fixed-dose regimens. |
| 13. | Gül | Does Lower Dose Pilocarpine Have a Role in Radiation-Induced Xerostomia? | 2024, 32 |
Lower-dose pilocarpine (5–15 mg/day) improves late-stage symptomatic xerostomia, with fewer adverse effects, providing a viable alternative to standard dosing. |
| 14. | Kapourani | A Review on the Role of Pilocarpine on the Management of Xerostomia and the Importance of the Topical Administration Systems Development | 2022, 33 |
Topical pilocarpine formulations, such as mouthwashes and lozenges, provide efficacy comparable to systemic administration while reducing systemic adverse effects, thereby enhancing patient adherence. |
| 15. | Hosseini | Cancer Treatment-Related Xerostomia: Basics, Therapeutics, and Future Perspectives | 2024, 34 |
This comprehensive review examines interventions for cancer treatment-related xerostomia, including cevimeline, and emphasizes the need for more robust clinical trials to confirm their efficacy and safety. |
| 16. | Alsahafi | Clinical evidence for managing radiotherapy-induced oral mucositis and xerostomia in head and neck cancer patients: a review of Phase III–IV trials | 2026 ,35 |
Review of meta-analysis confirming pilocarpine and cevimeline as principal pharmacological interventions for radiation-induced xerostomia, with significantly better efficacy than placebo. |
| S. No. | First Author | Full Title | Year, Citation | Findings |
|---|---|---|---|---|
| 17. | Cohen | Acupuncture for Chronic Radiation-Induced Xerostomia in Head and Neck Cancer: A Multicenter Randomized Clinical Trial | 2024, 39 |
True acupuncture improves symptomatic xerostomia and quality of life compared with standard oral hygiene, and these improvements last for 12 weeks. |
| 18. | Ni | Acupuncture for Radiation-Induced Xerostomia in Cancer Patients: A Systematic Review and Meta-Analysis | 2020, 40 |
Acupuncture improves symptomatic xerostomia, yet changes in salivary flow rates remain uncertain, and overall study quality is low. |
| 19. | Solarska | Recent Advances in the Prevention and Treatment of Post-Radiotherapy Xerostomia in Patients With Head and Neck Cancer | 2022, 41 |
Acupuncture may improve symptomatic xerostomia; however, effects on salivary flow rates remain unclear, and researchers need stronger evidence. |
| 20. | Dörfler | Umbrella Review: Summary of Findings for Acupuncture as Treatment for Radiation-Induced Xerostomia | 2023, 42 |
Acupuncture may alleviate symptomatic xerostomia, yet current evidence remains low in quality, and researchers need more rigorous studies. |
| S. No. | First Author | Full Title | Year, Citation | Findings |
|---|---|---|---|---|
| 21. | Salimi | Transcutaneous Electrical Nerve Stimulation to Treat Dry Mouth (Xerostomia) Following Radiotherapy for Head and Neck Cancer. A Systematic Review | 2021, 46 |
Transcutaneous ENS (TENS) is safe and feasible; initiating daily TENS concurrently with radiotherapy yields better outcomes. |
| 22. | Mercadante | Salivary Electrostimulation in the Treatment of Radiation Therapy–Induced Xerostomia (LEONIDAS-2): A Multicenter, Randomized, Double-Masked, Sham-Controlled, Phase 3 Trial | 2023 , 47 |
No differences are observed in primary or secondary outcomes; however, exploratory analyses indicate improvements in xerostomia subscale scores. |
| S. No. | First Author | Full Title | Year, Citation | Findings |
|---|---|---|---|---|
| 23. | Mosannen | Evaluation of the Effect of Photobiomodulation on Radiation-Induced Xerostomia in Head and Neck Cancer Patients: A Randomized Clinical Trial | 2024, 48 |
PBMT markedly increases stimulated saliva production and reduces patient-reported xerostomia compared with sham treatment. |
| 24. | Heiskanen | Photobiomodulation Therapy for Cancer Treatment-Related Salivary Gland Dysfunction: A Systematic Review | 2020, 49 |
Preliminary outcomes for patients receiving PBMT are positive; however, current evidence remains insufficient to determine its efficacy in managing cancer therapy-related xerostomia. |
| 25. | de Carvalho E Silva | Photobiomodulation for the Management of Xerostomia and Oral Mucositis in Patients With Cancer: A Randomized Clinical Trial | 2023, 50 |
PBMT improves quality of life and decreases patient-reported xerostomia severity compared with the control group. |
| 26. | Schepanski | Long-Term Evaluation of Salivary Glands After Photobiomodulation During Radiotherapy for Head and Neck Cancer | 2023 ,51 |
PBMT preserves salivary gland function during radiotherapy (RT), preventing reductions in salivary flow; however, some patients have experienced a decline 6 months post-RT. |
| 27. | Schepanski | Evaluation of Photobiomodulation Therapy (PBMT) on Salivary Flow and Composition in Head and Neck Cancer Patients Undergoing Radiation Therapy | 2024, 52 |
PBMT improves both salivary flow and composition, enhancing patient comfort during and post-RT. . |
| 28. | Lopez- Garzon Shrateh |
Photobiomodulation for restoring salivary flow after radiotherapy in head and neck cancer: a randomised placebo-controlled trial | 2025, 53 |
PBM therapy produced a clinically significant increase in unstimulated salivary flow. No adverse events recorded, suggesting potential regenerative effects |
| 29. | Shrateh | Treatment options for radiation-induced xerostomia in patients with head and neck cancer: a systematic review and meta-analysis |
2026, 54 |
PBMT statistically significantly reduced oral pain severity, consistent tissue-regenerative properties |
| S. No. | First Author | Full Title | Year, Citation | Findings |
|---|---|---|---|---|
| 29. | Philipsen | The Effect of Hyperbaric Oxygen Therapy in Head and Neck Cancer Patients With Radiation-Induced Dysphagia—A Systematic Review | 2024, 58 |
Evidence for the benefits of HBOT in patients with dysphagia after radiotherapy (RT) for head and neck cancer (HNC) is inconsistent. |
| 30. | Kumar | Radiation Effects in Head and Neck and Role of Hyperbaric Oxygen Therapy: An Adjunct To Management | 2024, 59 |
HBOT is effective in managing post-radiation changes in patients with HNC, including xerostomia. |
| S. No. | First Author | Full Title | Year, Citation | Findings |
|---|---|---|---|---|
| 31. | Chen | The Efficacy of Positioning Stents in Preventing Oral Complications After Head and Neck Radiotherapy: A Systematic Literature Review | 2020, 60 |
Evidence for preventing xerostomia in patients is weak, and more high- quality studies are needed. |
| 32. | Brandão | Are Intraoral Stents Effective In Reducing Oral Toxicities Caused By Radiotherapy? A Systematic Review And Meta-Analysis | 2021, 62 |
Use of intraoral stents notably reduces oral mucositis, salivary changes, and trismus in patients. |
| 33. | Kawakami | Effectiveness of Intraoral Stents in Reducing Oral Adverse Events During Radiotherapy for Maxillary or Nasal Cavity Malignant Tumors | 2024, 63 |
Intraoral stent use reduces the severity of oral mucositis, potentially benefiting xerostomia management in patients. |
| 34. | Alves | Benefits of Intraoral Stents in Patients With Head and Neck Cancer Undergoing Radiotherapy: Systematic Review | 2021, 64 |
Use of intraoral stents may help reduce oral mucositis, trismus, xerostomia, and radiation exposure to healthy tissues in patients. |
2.3. Risk-of-bias and Methodological Quality Assessment
The methodological quality and risk of bias of the included studies were assessed using tools appropriate for their study designs. Randomized controlled trials were evaluated using the Cochrane Risk of Bias 2 (RoB 2) tool, which considers bias arising from the randomization process, deviations from intended interventions, missing outcome data, measurement of outcomes, and selection of the reported results. Systematic reviews and meta-analyses were critically appraised using AMSTAR 2 (A Measurement Tool to Assess Systematic Reviews 2), which evaluates methodological quality across key domains including protocol registration, literature searching, study selection, risk-of-bias assessment, synthesis methods, and consideration of publication bias. The results of these assessments were incorporated into the interpretation of the evidence and are presented in the Results section and accompanying risk-of-bias figure.
3. RESULTS
3.1. Risk of Bias and Methodological Quality
The methodological quality of the included studies varied across study designs. Randomized controlled trials were evaluated using RoB 2, with judgments based on the five predefined bias domains. Systematic reviews and meta-analyses were assessed using AMSTAR 2. The principal methodological concerns across the evidence base included heterogeneity in outcome assessment, relatively small sample sizes in several intervention studies, variation in follow-up duration, and limitations in the reporting of study methods. Detailed RoB 2 domain-level assessments are summarized in Fig. (2).
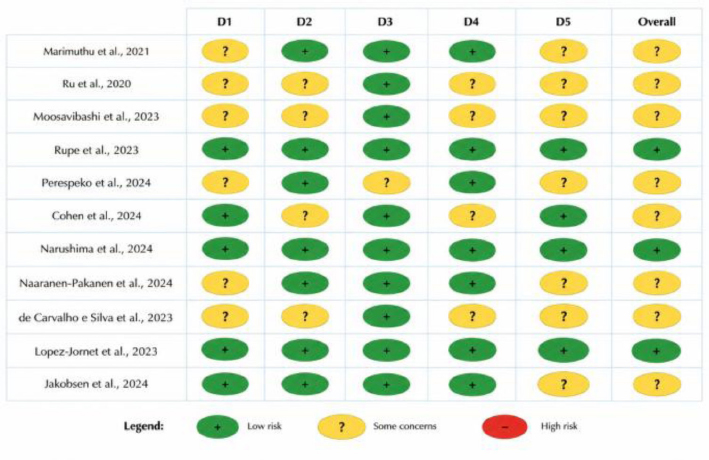
Risk-of-bias assessment of the included randomized controlled trials using the Cochrane Risk of Bias 2 (RoB 2) tool. D1, bias arising from the randomization process; D2, bias due to deviations from intended interventions; D3, bias due to missing outcome data; D4, bias in measurement of the outcome; D5, bias in selection of the reported result.
3.2. IMRT and Xerostomia
IMRT has been widely used for treating HNCs because of its ability to deliver targeted radiation while preserving the surrounding healthy tissue [8]. Evidence shows that IMRT lowers the incidence of RIX compared to conventional RT techniques [20]. IMRT is considered the standard of care for patients undergoing RT, given its effectiveness in reducing salivary gland dysfunction [3-7]. A 2020 meta-analysis by De Felice et al. compared IMRT with three-dimensional conformal RT (3D-CRT) in patients with head and neck squamous cell carcinoma and found that IMRT reduced the rate of xerostomia [21]. However, no notable differences were observed in overall survival or locoregional control between the two approaches [21]. A 2026 scoping review by Gerlach et al. found that a mean dose threshold below 25 Gy is required for meaningful functional recovery; above this threshold, salivary flow is markedly reduced, with minimal or no long-term recovery, underscoring the critical importance of IMRT [22]. The characteristics and main findings of studies evaluating IMRT and proton beam therapy are summarized in Table 2.
3.3. PBT and Xerostomia
PBT, particularly intensity-modulated proton therapy (IMPT), provides dosimetric advantages over photon-based therapies, such as IMRT, by delivering highly conformal radiation with a minimal exit dose. This precision helps protect the salivary glands and reduces the risk of RIX [9]. In a 2021 study, Cao et al. [20] compared IMPT with IMRT in patients with oropharyngeal cancer and revealed that IMPT was associated with markedly lower rates of xerostomia at 18–24 and 24–36 months post-treatment. Moreover, study findings showed that dosimetric variables related to the oral cavity were more strongly associated with late xerostomia than those related to the salivary glands [20].
Yahya et al. [23] have conducted a systematic review on quality of life and patient-reported outcomes after proton therapy for oropharyngeal carcinoma. Patients who received IMPT reported better outcomes regarding xerostomia, particularly in the physical and personal domains, than those treated with IMRT [23].
In 2022, Youssef et al. compared IMPT with IMRT in non-metastatic oropharyngeal carcinoma and found that IMPT was associated with lower rates of xerostomia and improved patient-reported outcomes. Survival outcomes were similar between the two groups [24]. The main findings of studies evaluating PBT and Xerostomia are summarized in Table 2.
3.4. Comparison of IMRT and PBT
IMRT and PBT show strong effectiveness in reducing xerostomia in patients receiving treatment for HNC [20-23]. IMRT offers essential advantages over conventional techniques, such as 3D-CRT, by sparing salivary glands and lowering xerostomia rates [21]. PBT provides an improved dose distribution, leading to further reductions in xerostomia rates, particularly over long-term periods [9]. Access to PBT and its higher cost remain major considerations for treatment planning [9, 20-24]. Current evidence supports the value of PBT, and additional randomized controlled trials (RCTs) will help clarify its long-term benefits and any potential disadvantages compared with IMRT [24].
3.5. Supportive Care with Artificial Saliva and Oral Moisturizers
Artificial salivary products and oral moisturizers provide standard supportive care for xerostomia by relieving symptoms without restoring natural salivary function. Substitutes are available as moisturizing gels, mouth sprays, toothpastes, or mouthwashes [18, 25]. A systematic review conducted by Assery [18] found that these products alleviated symptomatic xerostomia, with benefits varying according to patient needs and preferences [7]. A 2021 study by Marimuthu et al. showed that artificial saliva substitutes relieve RIX in patients with HNC. Trehalose-based sprays improve salivary pH and flow with efficacy comparable to traditional carboxymethylcellulose sprays. Immunologically active substitutes enhance patient-reported xerostomia scores and salivary flow compared to placebo [26].
Nuchit et al. (2020) have shown that continuous use of saliva substitutes improves swallowing ability and nutritional status in patients who have completed RT for HNC [27]. Edible saliva gels and oral moisturizing jellies reduce Candida colonization and enhance salivary properties. Patient preferences for saliva substitutes depend on their taste and ease of use. All tested substitutes relieved symptomatic xerostomia, with individual preferences influencing adherence and satisfaction [28].
Integrated supportive programs that include oral hygiene education and lifestyle modifications enhance salivary flow and alleviate symptomatic xerostomia, as shown in a 2023 systematic review by Lanzetti et al. [29]
The sodium–hyaluronate mouthwash improves xerostomia symptoms and quality of life without adverse effects, as shown in a study by Rupe et al. (2023) [30]. Its film-forming properties rehydrate and protect oral tissues. Salivary substitutes with enzymatic systems have demonstrated some improvement in xerostomia symptoms. However, the differences were not statistically significant when compared with placebo, and further research is needed to confirm their efficacy [30].
A personalized approach that considers the variety of saliva substitutes and individual patient factors is essential for the effective management of RIX in patients with HNC [18, 25-31]. The characteristics and key findings of studies evaluating artificial saliva substitutes and oral moisturizers are summarized in Table 3.
3.6. Pharmacological Interventions: Pilocarpine, Cevimeline, and Amifostine
3.6.1. Pilocarpine and Cevimeline
Pilocarpine and cevimeline are muscarinic agonists that stimulate salivary secretion and are widely used to manage RIX [10-13]. Studies have explored dosing strategies to optimize efficacy and minimize adverse effects [10-17]. Watanapokasin et al. (2024) have shown that as-needed pilocarpine effectively relieves symptomatic xerostomia with fewer adverse effects and lowers treatment costs than fixed-dose regimens [17]. Gül et al. (2024) reported that lower-dose pilocarpine at 5–15 mg/day improves late-stage symptomatic xerostomia with fewer adverse effects, providing a viable alternative to standard dosing [32].
Pilocarpine effectively stimulates salivary flow, and flexible dosing options help minimize adverse effects [32]. Potential adverse effects, including sweating, nausea, and cardiovascular reactions, can reduce patient adherence [10-17, 32]. To limit systemic adverse effects, research has focused on developing topical pilocarpine delivery systems, such as mouthwashes, lozenges, pastilles, sprays, and buccal inserts [33].
Clinical studies have revealed that topical formulations effectively increase salivary flow and alleviate symptomatic xerostomia with minimal systemic absorption, resulting in fewer adverse effects, as demonstrated by Kapourani et al. (2022) [33]. Pilocarpine mouthwashes and lozenges notably improve salivary secretion and patient comfort, offering efficacy comparable to systemic administration while improving tolerance [33]. Furthermore, cevimeline has been evaluated for its efficacy in managing RIX [12].
In two double-blind, placebo-controlled trials, cevimeline 30–45 mg thrice daily increased unstimulated salivary flow compared to placebo. One study showed improvement in patient-reported symptomatic xerostomia, whereas the other did not, possibly due to a high placebo response rate [12]. A long-term, open-label study conducted over 52 weeks found that cevimeline 45 mg three times daily is generally well tolerated, with 59.2% of patients reporting improvement in symptomatic xerostomia [13].
Cevimeline is generally well tolerated, with common adverse events including nausea, diarrhea, and sweating, the latter reported in 47.5% of patients [13]. Regarding long-term use, 17.6% of patients discontinued treatment due to adverse events, most frequently due to sweating [13]. While cevimeline improves salivary flow and patient-reported symptoms, clinicians should monitor for potential adverse effects, particularly increased sweating, and consider individual tolerance when prescribing this medication [12, 13].
A meta-analysis involving cevimeline and pilocarpine has revealed that both relieve symptomatic xerostomia and increase salivary flow compared with placebo. Nonetheless, the clinical relevance and significance of these findings require further study [6]. Both medications enhanced salivary secretion, with no differences in efficacy or adverse effects [14]. A 2024 comprehensive review by Hosseini et al. examined interventions for cancer treatment-related xerostomia, including pilocarpine and cevimeline, and highlighted the need for more robust clinical trials to confirm their efficacy and safety [34]. A 2026 review of meta-analyses by Alsahafi et al. concluded that pilocarpine and cevimeline had significantly superior efficacy than placebo in enhancing salivary secretion, recognizing them as the primary pharmacological interventions for radiation-induced xerostomia [35].
3.6.2. Amifostine
Amifostine is a cytoprotective agent that scavenges free radicals and protects normal tissue from radiation-induced damage. A systematic review and meta-analysis of 17 RCTs involving 116 patients showed that amifostine lowered the risk of developing acute and late xerostomia [16]. A 2-year follow-up study showed that administering amifostine during RT reduced the severity and duration of xerostomia without affecting tumor control or survival [15].
Amifostine can cause nausea, vomiting, hypotension, and allergic reactions; however, these effects are generally manageable [15, 16]. Typically administered intravenously at 200 mg/m2 15–30 min before each radiation fraction, this agent protects against acute and late xerostomia without affecting tumor control [15, 16]. Intravenous administration requires monitoring for potential adverse effects. The overall benefit of amifostine in patients with HNC remains debated, and further research is needed to optimize dosing and explore combination therapies to improve efficacy and tolerability [15, 16]. The included studies evaluating pharmacological interventions for radiation-induced xerostomia are summarized in Table 4.
3.7. Non-pharmacological Approaches: Acupuncture, Electrical Nerve Stimulation (ENS), PBMT, HBO, and Intraoral Stents
3.7.1. Acupuncture
Acupuncture may relieve symptomatic xerostomia by stimulating salivary gland function through neuromodulation. Needle insertion at specific points can activate the parasympathetic nervous system and enhance salivary secretions. Additionally, acupuncture may affect the central nervous system pathways, altering the perception of xerostomia [36]. Findings of a long-term follow-up study have revealed that 24 acupuncture treatments over 6 months improved unstimulated salivary flow rates, with sustained benefits for up to 3 years [36].
However, a Cochrane review demonstrated that, despite a small increase in salivary production, the evidence is insufficient to support the use of acupuncture for improve xerostomia [37]. Similarly, a systematic review conducted in 2018 has revealed inadequate evidence for using acupuncture in patients with xerostomia [38].
A 2024 multicenter RCT by Cohen et al. showed that acupuncture improves symptomatic xerostomia and quality of life compared with standard oral hygiene, with these positive effects sustained for 12 weeks post-treatment. Moreover, acupuncture is generally well tolerated, with manageable adverse effects such as facial edema, flu-like symptoms, joint pain, hypertension, headaches, and bruising [39].
A systematic review and meta-analysis by Ni et al. in 2020 found that acupuncture improves patient-reported xerostomia, yet does not increase stimulated or unstimulated salivary flow rates [40]. Solarska and Żylicz (2023) demonstrated that acupuncture may relieve symptomatic xerostomia, while the effects of acupuncture on salivary flow remain inconclusive and require more robust evidence [41]. Another review, by Dörfler et al., noted the low quality of existing studies due to small sample sizes, lack of blinding, and heterogeneity in study designs [42].
Placebo effects remain possible, as several studies have demonstrated improvements in both true and sham acupuncture groups [39, 42, 43]. The variability in acupuncture techniques, points selected, and treatment durations across studies limits the ability to draw definitive conclusions [40, 42]. Therefore, high-quality large-scale RCTs with standardized protocols are required to clarify the efficacy and underlying mechanisms of acupuncture. Clinical evidence concerning the use of acupuncture for radiation-induced xerostomia is detailed in Table 5.
3.7.2. ENS
ENS, including transcutaneous ENS (TENS) and intraoral neuroelectrostimulation, aims to enhance salivary gland function by stimulating nerves that support salivation. TENS delivers mild electrical currents through the skin to target the parotid and submandibular glands, whereas intraoral devices provide stimulation from within the oral cavity [44]. An RCT involving 68 patients showed that TENS improved stimulated salivary flow, patient perception of salivary flow, and quality of life over 6 months [45].
A systematic review by Salimi et al. in 2021, encompassing five studies and 280 patients, concluded that TENS is a safe and feasible approach for managing xerostomia, with the greatest benefit when initiated concurrently with RT [46]. Conversely, the LEONIDAS-2 Phase 3 trial by Mercadante et al. in 2023 evaluated an intraoral neuroelectrostimulation device over 12 months and observed no clear differences between the active and sham devices. Exploratory analysis indicated improvement in xerostomia subscale scores in quality-of-life assessments [47].
Across the reviewed studies, ENS therapies, including TENS and intraoral devices, were largely well tolerated with minimal adverse effects [44, 45]. No serious adverse effects have been reported, which supports a favorable safety profile [45-47]. Differences in stimulation parameters, session durations, and electrode placements across studies limit the ability to standardize treatment protocols [45-47]. Several studies included sample sizes, which may affect the generalizability of the results. Large-scale, long-term RCTs are required to clarify the sustained efficacy and safety of ENS therapies in this patient population. Studies assessing electrical nerve stimulation as a therapeutic approach for xerostomia are outlined in Table 6.
3.7.3. PBMT
PBMT, alternatively called low-level laser therapy, uses non-ionizing light sources, including lasers and light-emitting diodes, to stimulate cellular functions. Regarding xerostomia, PBMT is thought to enhance salivary gland function by promoting cellular metabolism, reducing inflammation, and improving microcirculation, thereby counteracting radiation-induced damage [48]. A 2020 systematic review by Heiskanen et al. revealed positive preliminary results, yet concluded that current evidence is insufficient to determine the efficacy of PBMT for managing cancer therapy-related xerostomia [49].
Similarly, the 2021 guidelines jointly issued by the International Society of Oral Oncology (ISOO), Multinational Association of Supportive Care in Cancer (MASCC), and American Society of Clinical Oncology (ASCO), authored by Mercadante et al., concluded that evidence remains insufficient to recommend for or against low-level laser therapy during RT for HNC [7]. In an RCT, de Carvalho E Silva et al. (2023) showed that PBMT improves patients' quality of life and reduces the severity of xerostomia compared with the control group [50]. Another 2023 study evaluated long-term effects during RT, concluding that PBMT preserves salivary gland function and prevents reductions in salivary flow [51]. However, a decline was observed 6 months post-RT [51].
A 2024 study by Schepanski et al. evaluated the impact of PBMT on salivary flow and composition in patients with HNC undergoing RT. The study found that PBMT improved both salivary flow and composition, enhancing patient comfort during and after treatment [52]. In a 2025 study by Lopez-Garzon et al., a randomized, placebo-controlled trial found that PBM therapy produced a clinically significant improvement in unstimulated salivary flow in patients with chronic post-radiation-induced xerostomia, and no adverse events were reported, suggesting potential regenerative effects on the salivary glands [53]. Overall, across the reviewed studies, PBMT was typically well tolerated with minimal adverse effects and no serious adverse events, indicating a favorable safety profile [51, 52]. However, variations in PBMT protocols, including wavelength, dosage, and treatment duration, limit the ability to standardize treatment. Some studies had small sample sizes, potentially affecting the generalizability of the findings [49, 50, 52]. A 2026 meta-analysis by Shrateh et al. stated statistically significant reductions in oral pain severity across studies included PBMT, consistent with the tissue-regenerative properties of PBMT [54]. Although short-term benefits are evident, long-term efficacy and sustainability require further investigation. The available studies examining photobiomodulation therapy and its effects on salivary function are presented in Table 7.
3.7.4. HBOT
The role of HBOT in xerostomia remains controversial [55]. Several studies involving patients who have undergone RT for HNC have reported improvements in salivary flow rates and symptomatic xerostomia. HBOT is thought to enhance vascularity and mobilize stem cells, potentially improving salivary gland function [55, 56]. The therapy involves breathing 100% oxygen at elevated atmospheric pressure, increasing oxygen dissolution in the plasma. This hyperoxia can stimulate angiogenesis, fibroblast proliferation, and collagen synthesis, potentially restoring function in irradiated salivary glands [57].
Several studies have found that HBOT can improve both unstimulated and stimulated salivary flow rates, reducing the severity of symptomatic xerostomia [58]. Patients who undergo HBOT have reported improvements in oral comfort and overall quality of life, which are attributed to increased salivary flow and reduced dryness. Not all patients experience these benefits, and the degree of improvement may vary based on individual factors, such as the extent of salivary gland damage and the time since completing RT [59].
A systematic review by Philipsen et al. (2024) assessing the role of HBOT in patients with post-RT dysphagia noted inconsistent evidence of its benefits [58]. Another study by Vijay Kumar et al. (2024) demonstrated that HBOT is effective in managing post-radiation changes in patients who have undergone treatment for HNC, including RIX [59]. Although current studies are promising, larger RCTs are needed to establish standardized protocols and confirm their long-term efficacy. Evidence regarding the application of hyperbaric oxygen therapy in patients with radiation-related oral complications is summarized in Table 8.
3.7.5. Intraoral Stents
Intraoral stents reposition oral structures to reduce radiation to non-target tissues, including the salivary glands. This spatial displacement helps preserve salivary gland function and decreases the incidence and severity of RIX [60]. In an RCT, Mall et al. observed that patients who used positioning stents exhibited higher unstimulated and stimulated salivary flow rates at 3 and 6 months post-RT than controls, and subjective assessments indicated improvement in symptomatic xerostomia in the stent group [61].
A systematic review by Chen et al. [60] emphasized the weak evidence supporting positioning stents for xerostomia prevention and called for more high-quality, prospective trials with long-term follow-up [60]. Recent systematic reviews and clinical studies have consistently demonstrated the clinical utility of intraoral stents. Brandão et al. found that these devices significantly reduce the incidence of oral mucositis, trismus, and changes in salivary flow in patients undergoing radiotherapy [62]. Furthermore, a 2024 study by Kawakami et al. highlighted that stent use specifically reduces the severity of oral mucositis in patients with maxillary or nasal cavity malignancies, which may offer secondary benefits for the long-term management of dry mouth [63]. Supporting these findings, Alves et al. confirmed that stents minimize radiation exposure to healthy tissues, thereby mitigating common toxicities such as xerostomia and oral mucositis [64]. The current evidence is still limited, and additional research is required to establish standardized protocols and confirm their long-term efficacy. Clinicians should consider using intraoral stents on a case-by-case basis, taking into account patient-specific factors and resource availability. Table 9 highlights studies evaluating the role of intraoral stents in reducing radiotherapy-associated oral complications, including xerostomia.
3.8. Surgical Interventions
Submandibular gland transfer relocates the submandibular salivary gland to an area external to the radiation field, typically the submental space, to preserve gland function during RT. This procedure has shown promise in decreasing the incidence and severity of xerostomia. However, the procedure is primarily applicable to patients scheduled for postoperative RT, and its success depends on surgical expertise and patient selection [65]. Another approach involves autotransplanting salivary gland tissue, relocating glands or their components external to the radiation field, or both, to preserve function. Jeon et al. [66] have investigated transplantation of salivary gland organoids derived from stem cells, as a therapeutic option for RIX. These organoids restored salivary function in animal models, suggesting their potential for clinical application [66]. Shrateh et al.'s meta-analysis concluded that salivary gland transfer and new regenerative therapies, including stem cell–based approaches, show promising therapeutic potential. However, the available evidence are limited, highlighting the need for larger clinical studies [54]. Studies investigating surgical and regenerative approaches for restoring or preserving salivary gland function are summarized in Table 10.
| S. No. | First Author | Full Title | Year, Citation | Findings |
|---|---|---|---|---|
| 35. | Jeon | Salivary Gland Organoid Transplantation as a Therapeutic Option For Radiation-Induced Xerostomia | 2024, 66 |
The study demonstrates that transplantation of salivary gland organoids restores salivary function in animal models with radiation-induced xerostomia (RIX). |
| 36. | Jakobsen | Mesenchymal Stem/Stromal Cell Therapy for Radiation-Induced Xerostomia in Previous Head and Neck Cancer Patients: A Phase II Randomized, Placebo-Controlled Trial | 2024, 67 |
This study assesses the efficacy of stem cell therapy in improving salivary function in patients after radiotherapy (RT). |
| 37. | Jakobsen | Long-Term Outcome Following Treatment With Allogeneic Mesenchymal Stem/Stromal Cells for Radiation-Induced Hyposalivation and Xerostomia | 2024, 68 |
A 3-year follow-up study demonstrates that allogeneic MSC therapy is safe and results in marked improvements in stimulated salivary flow rates and patient-reported symptomatic xerostomia, with no treatment-related serious adverse events or long-term immunogenic responses observed. |
| 38. | Li | Mesenchymal stem cell therapy for radiation-induced xerostomia: a systematic review and network meta-analysis | 2026, 69 |
MSC therapy results in a statistically significant improvement in unstimulated salivary flow, with no significant improvements in clinical or stimulated flow, or in xerostomia scores. |
| 39. | Guan | Efficacy of Mesenchymal Stem Cell Therapy in Rodent Models of Radiation-Induced Xerostomia and Oral Mucositis: A Systematic Review | 2023, 70 |
Systematic review indicating that mesenchymal stem cell (MSC) therapy improves salivary flow rates and reduces tissue damage in rodent models with RIX. |
Mesenchymal stem/stromal cell (MSC) therapy has emerged as a promising approach for restoring salivary gland function in patients whose glands are damaged by radiation [67]. In a Phase II randomized, placebo-controlled trial, Jakobsen et al. evaluated allogeneic adipose-derived MSC injections into the submandibular glands of patients with RIX. The study found improvements in salivary flow rates and patient-reported symptomatic xerostomia compared to the placebo group [67].
Furthermore, a long-term follow-up study by the same research group assessed the safety and efficacy of MSC therapy over 3 years. This study found sustained improvements in salivary function without serious adverse events, highlighting MSC therapy as a potentially durable treatment option. In addition, preclinical studies have demonstrated the potential of MSC therapy in animal models [67, 68].
A systematic review by Guan et al. [69] analyzed the efficacy of MSC therapy in rodent models and the incidence of RIX and oral mucositis. A review concluded that MSC treatment improved salivary flow rates and reduced tissue damage, supporting the translational potential of this therapy [68]. However, a 2026 meta-analysis by Li et al. of clinical trials found that MSC therapy resulted in a statistically significant but clinically limited improvement in unstimulated salivary flow and didn’t demonstrate significant improvement in stimulated salivary flow or patient-reported xerostomia scores [70]. Collectively, these studies suggest that both autotransplantation of salivary gland tissue and MSC therapy hold promise for managing RIX [70]. However, further clinical trials are needed to establish standardized protocols and to confirm their long-term efficacy and safety.
4. DISCUSSION
This systematic review evaluated the impact of various preventive and therapeutic strategies on radiation-induced xerostomia (RIX) in patients with head and neck cancer (HNC). Substantial evidence demonstrates that advanced radiotherapy techniques, including intensity-modulated radiation therapy (IMRT) and proton beam therapy (PBT), markedly decrease the rate of radiation-induced xerostomia (RIX) in patients with head and neck cancer on comparison with conventional approaches such as three-dimensional conformal radiation therapy (3D-CRT) [21]. This study shows that IMRT was associated with a lower grade of acute xerostomia, and there was a significant difference in late xerostomia between 3D-CRT and IMRT at 1 year and 2 years after treatment [21]. Compared with photon therapy, proton beam therapy (PBT), particularly Intensity-Modulated Proton Therapy (IMPT), provides superior dosimetric advantages over IMRT by delivering lower oral cavity, mean larynx, and mean parotid gland doses than in patients treated with IMRT [24]. The same study shows that IMPT treatment was associated with a significantly lower likelihood of developing grade 2 or higher acute AEs than IMRT [24]. One report shows that IMPT has lower rates of late xerostomia than IMRT [20]. When death was included as a competing risk, the locoregional failure-free survival between the IMPT and IMRT groups was estimated to be similar and not statistically different [24]. The main drawback of proton therapy is the high cost of constructing a cyclotron and maintaining the facility [23].
In the 35 studies included, the hierarchy of evidence indicates that IMRT/IMPT is the cornerstone of RIX prevention, while pharmacologic is used as second-line symptomatic therapy and non-pharmacologic/regenerative for refractory or recovery-targeted situations. Whilst a small increase in salivary flow has been reported with pilocarpine and cevimeline, their efficacy was modest, and compliance was hindered by cholinergic side-effects, consistent with the findings of the Cheng meta-analysis [10] and those of Alsahafi et al. [35]. The evidence regarding the efficacy of the non-pharmacologic modalities is less consistent: photobiomodulation seems to be most effective with concurrent radiotherapy, TENS is showing benefits only in extra-oral application, and acupuncture trials are still heterogeneous and have significant placebo effects. While promising, surgical gland transfer and MSC therapy are both investigational and need long-term safety data before they can be recommended as guidelines. Importantly, there is no single modality that can provide complete radiation sparing, and symptom-targeted interventions are additive, providing durable benefit from the radiation-sparing component. Such a synthesis should be used to inform shared decision-making with patients and to support the development of institution-specific RIX management pathways. Authors' cautious recommendations were supported by moderate confidence in the evidence for radiotherapy planning, modest confidence in the evidence for pharmacological agents, and low to very low confidence in the evidence for regenerative therapies, as assessed using RoB 2 and AMSTAR-2.
Artificial saliva and oral moisturizer products are widely used as standard supportive management for radiation-induced xerostomia (RIX). Across the reviewed studies, all substitutes consistently reduced symptomatic xerostomia, increased salivary pH and flow, and improved quality of life without causing side effects. One study comparing herbal formulations with Hypozalix reported that the group receiving herbal compounds experienced improvement in more xerostomia-related symptoms and quality-of-life domains than the Hypozalix group; however, the lack of objective outcome measures may introduce bias [18]. The same study showed that bioXtra gel increased salivary pH and Candida counts [18]. Another study of patient preference data indicated that gel, mucin, and carmellose were each favored by approximately 27% of patients, while oil was preferred by 17.5%; about 55% wished to continue using carmellose spray compared with 42% for oil [25]. The main results of the randomized controlled trial demonstrated that sodium–hyaluronate mouthwash is effective in reducing the burden of radiation-induced xerostomia symptoms [30].
Current evidence shows that both pilocarpine and cevimeline are effective for managing radiation-induced xerostomia (RIX); both drugs have similar effects on salivary flow and patient-reported symptoms, with no significant difference in overall efficacy [14]. Cevimeline's greater M3 receptor selectivity is thought to give it a better side-effect profile; however, studies have not demonstrated a marked difference in adverse events between these agents [6, 12, 13, 14]. Pilocarpine provides clinical benefit through adjustable dosing and topical formulations that reduce systemic side effects while preserving effectiveness [17, 32, 33]. Methods for delivering cevimeline have not advanced as much as might be expected, given individual perceptions of xerostomia assessment and the potential for placebo effects, as seen especially in cevimeline studies, which complicate direct comparisons [12]. Treatment choice should be individualized by tolerability, dosing flexibility, and patient preference. Larger, well-controlled studies are needed. These will help optimize long-term outcomes and clarify comparative benefits of these agents [6, 34].
Amifostine is a radioprotector initially developed as part of the nuclear warfare programs. One study demonstrated that the drug was delivered by intravenous injection and only one by subcutaneous injection, suggesting that hypodermic administration of the drug may substantially reduce these side effects [16]. The incidence of Grade 2 chronic xerostomia was significantly lower in the amifostine group at each visit compared to the control group [15]. Longitudinal analysis of overall quality-of-life scores indicated a net benefit with amifostine, with this difference approaching statistical significance over two years of follow-up [15]. Progression-free survival rates did not differ significantly between the amifostine and control groups at any time point. Similarly, overall survival did not differ significantly between groups at any measurement interval [15]. Longitudinal analysis demonstrated that patients treated with amifostine were significantly more likely to exhibit meaningful unstimulated saliva production during the one- to two-year post-treatment period [15]. The potential reduction of radiation-induced toxicities by amifostine must be balanced against the risk of amifostine-related toxicities within the context of each patient's treatment strategy [16].
Although the mechanisms underlying acupuncture are not fully understood, evidence from multiple studies suggests potential central nervous system effects mediated by fascial manipulation [39]. Additionally, studies have demonstrated a significant increase in blood flow in the cheek skin of patients with xerostomia [39]. At the end of the treatment period, a meta-analysis of three clinical trials investigating acupuncture found increased stimulated whole saliva production in the acupuncture groups [37]. The stimulated salivary flow rate did not differ significantly between the real acupuncture and sham acupuncture groups. The unstimulated salivary flow rate was not improved in the real acupuncture group compared with the sham acupuncture group [40]. Findings regarding the effect on objective salivary flow rates remain inconsistent. The overall evidence is constrained by study heterogeneity, potential placebo effects, and methodological limitations. High-quality, large-scale randomized controlled trials are necessary to confirm these results.
Extraoral TENS use is consistently effective for radiation-induced xerostomia, while the benefits of intraoral TENS use are more uncertain. A randomized trial by Dalbem Paim et al. demonstrates a beneficial effect of a brief, tailored TENS protocol, with long-term improvements in stimulated salivary flow and xerostomia-related quality of life, suggesting a rehabilitative rather than merely palliative effect of TENS [45]. Given these and other trials, Salimi et al. found that neither conventional TENS nor ALTENS showed any significant adverse effects, and they were both safe and feasible, often comparable with pharmacologic sialogogues, but noted a significant heterogeneity in electrode placement, parameters, and timing, which prevented them from defining an optimal protocol [46]. The LEONIDAS 2 phase 3 trial, on the other hand, did not show any clinically relevant difference between a long-term intraoral neuro electrostimulation device and sham for most salivary and quality-of-life outcomes, and only for limited gains in symptom level [47]. All of these results suggest that the efficacy of ENS is very sensitive to modulation type, type of stimulation site, timing of stimulation, and the importance of establishing standard ENS/ALTENS protocols and conducting more high-quality trials before ENS becomes a routine standard of care for any guidelines.
In the short term, photobiomodulation therapy (PBMT) has demonstrated positive results in decreasing the severity of xerostomia, enhancing saliva flow and quality of life, and has been well tolerated overall [52]. Evidence is, however, limited and inconsistent, and much of it is related to the weak long-term efficacy seen, which is partly due to differences in treatment protocols and study design. Thus, more high-quality RCTs are needed. Other studies have shown that stimulated saliva flow rate was higher in the case group and that subjective xerostomia was lower after the sixth follow-up session following photobiomodulation (PBM) treatment. This decrease was observed in the 4th, 5th, and 6th weeks [48]. The unstimulated salivary levels were higher in the case group than in the control group at follow-up, but this difference was not statistically significant. In particular, week six showed a statistically significant improvement in stimulated saliva [48]. The best laser settings to preserve salivary gland function are not yet known.
HBOT is known to increase vascularity, which helps prevent ischemic tissue damage [59]. Overall, patients undergoing HBOT have a significantly improved quality of life in the short term (0–6 weeks after treatment) compared to patients not undergoing HBOT. But at 1 year, patients in the HBOT group had slightly worse QoL scores than those in the placebo group [55]. In contrast, non-HBOT patients had somewhat variable but generally constant viscosity scores, whereas HBOT patients showed a negative correlation between treatment time and saliva viscosity, indicating progressive improvement [55]. Patients under HBOT also report a heightened sensation of dry mouth, whereas controls experience a slight worsening of dry mouth over time [55]. No increase in salivary flow rate has been shown with HBOT in a mouse model in vivo [56]. In another clinical study, patients with late soft-tissue radiation injury of the salivary glands experienced considerable subjective and objective improvement in xerostomia after undergoing HBOT [57]. Other studies demonstrated improved mouth opening, decreased discharge, and improved sinus drainage, but fistula closure and osteomyelitic changes were not statistically significant and may have required further procedures [59].
The purpose of intraoral stents is to reshape and secure oral tissues during radiotherapy, thereby minimizing acute and late effects in these areas including the oral mucosa, salivary glands and mandible [60-64]. Systematic reviews and clinical studies provide a consistent body of evidence that these devices can significantly reduce the incidence and severity of oral mucositis, trismus, and salivary changes in head and neck radiotherapy, demonstrating their clinical utility within toxicity-reduction strategies [62-64]. However, whether intraoral stents prevent xerostomia is unclear. In the absence of high-quality evidence, Chen et al. concluded that it had no preventive role for xerostomia and highlighted the need for more comprehensive, longer-term randomized and prospective trials [60]. However, positioning stents have been shown to increase unstimulated and stimulated salivary flow and improve xerostomia-related symptoms in an RCT by Mall et al., suggesting that the benefits may be context- and site-specific rather than universal [61]. Within the last decade, some systematic reviews and clinical studies have confirmed the benefit of intraoral stents to reduce the radiation dose to healthy oral tissues and to decrease the incidence or severity of oral mucositis, as well as other advantages such as trismus and salivary function, including in the maxillary and nasal cavity tumors [62-64]. However, differences in study data due to variable stent designs, tumor locations, radiotherapy techniques, and outcome measures make it difficult to draw general conclusions or establish consistent protocols [60-64]. Overall, intraoral stents appear to be low-risk adjuncts, with potential clinical benefits, when applied selectively [60-64]. Additional high-quality evidence is needed to better define their long-term outcomes and to substantiate guideline-level recommendations.
The available and reviewed evidence has some limitations and should be considered. The studies included are very heterogeneous in design, radiotherapy techniques, dosimetry, sample size, and follow-up period, complicating direct comparison and the carrying out of a meta-analysis. Another point of concern is that numerous trials of newer or supportive therapies such as ENS, PBMT, intraoral stents, and cellular therapies are small, sometimes single-center, and lack sufficient power to assess long-term outcomes or less common adverse effects. This English-language time limit from 2020 to 2025 also introduces language and publication bias and may not capture pre-existing foundational research.
Well-designed multicenter, randomized controlled trials with uniform outcome assessments (both subjective scales and objective salivary tests), and sufficient long-term follow-up are needed. Mesenchymal stem cells (MSCs) appear to be a more uniform stem cell therapeutic option [70]. However, data suggest that MSCs may reduce apoptosis, increase salivary protein expression, and promote markers of tissue repair, thereby restoring salivary flow and tissue healing [69]. Future studies need to work towards unifying sources of MSCs and treatment guidelines to improve the management of radiation-induced xerostomia and oral mucositis [69]. However, the clinical efficacy of adipose-derived mesenchymal stem/stromal cells (ASCs) is still uncertain [67, 68]. Improvements in certain measures, such as saliva flow rate and decreased saliva viscosity, have been reported, but these were only short-term and failed to achieve meaningful long-term improvements in function or quality of life. This implies that additional optimization of treatment protocols, such as dosage and frequency, is needed [67, 68]. New gene therapy strategies, such as viral vector-mediated aquaporin-1 gene delivery and CRISPR-Cas9 gene editing, have shown promising preclinical results in restoring salivary gland function following radiotherapy. Nevertheless, their clinical use is still restricted and further studies are required before their use can be recommended in practice [71]. The literature reviewed here has several important gaps. There is a lack of standardized outcome measures, which limits comparability across studies. Non-pharmacological intervention studies are further constrained by small sample sizes. Regenerative therapies, including MSC- and ASC-based approaches, lack long-term follow-up, so the durability of any functional or quality-of-life benefit remains unestablished. Finally, head-to-head comparisons between IMPT and IMRT are needed to define their relative advantages.
CONCLUSION
This study reviewed 35 studies published between 2020 and 2025 that evaluated preventive and therapeutic strategies for radiation-induced xerostomia in patients with head and neck cancer. Advanced radiotherapy techniques, particularly intensity-modulated radiotherapy (IMRT) and intensity-modulated proton therapy (IMPT), were associated with sustained reductions in xerostomia. Pilocarpine, cevimeline, and amifostine remained the principal pharmacologic interventions, while photobiomodulation, electrical nerve stimulation, acupuncture, and intraoral stents showed potential as adjunctive therapies in selected patients. Overall, the evidence supported a shift toward individualized, multimodal management strategies aimed at preserving salivary function and improving long-term quality of life. Future studies should prioritize well-designed, adequately powered clinical trials that compare multimodal treatment strategies and establish standardized outcome measures for salivary function and patient-reported xerostomia. Mesenchymal stem cell therapy and submandibular gland transfer have shown promising mechanistic rationale and preliminary safety; however, further clinical evidence is required before they can be recommended for routine practice. Future research should also identify patient-specific factors that can guide treatment selection and support the development of personalized prevention and management pathways.
Future recommendations. Future research should focus on: (i) multicenter, appropriately sized and powered randomized controlled trials with patient-centred outcome measures (e.g., XQ and unstimulated salivary flow) and follow-up longer than 24 months; (ii) head-to-head comparisons between IMPT and IMRT in anatomically suitable populations with HNC; (iii) optimization of dosing, timing and route of administration for pharmacologic and non-pharmacologic interventions; (iv) standardization of photobiomodulation and electrical-stimulation protocols to facilitate pooling across studies; and (v) translational programs for MSC and gene-therapy approaches with a long-term safety framework that is compliant with regulatory guidelines. Incorporating these priorities into international HNC survivorship guidelines will hasten patient-centred care and decrease the worldwide burden of xerostomia caused by radiation therapy.
AUTHORS’ CONTRIBUTIONS
The authors confirm their contributions to the paper as follows: M.A. Had the idea for the study; the idea was approved throughout the research process, and the manuscript was critically revised. H.A.: Wrote the research and edited the manuscript; Y.A. and N.A. wrote the manuscript.
LIST OF ABBREVIATIONS
| ASCO | = American Society of Clinical Oncology |
| ENS | = Electrical nerve stimulation |
| HNC | = Head and neck cancer |
| IMPT | = Intensity-modulated proton therapy |
| ISOO | = International Society of Oral Oncology |
| ISU | = Investigator Support Unit |
| MASCC | = Multinational Association of Supportive Care in Cancer |
| MSC | = Mesenchymal stem cell |
| PBT | = Proton beam therapy |
| PRISMA | = Preferred Reporting Items for Systematic Reviews and Meta-Analyses |
| RCT | = Randomized controlled trial |
| RIX | = Radiation-induced xerostomia |
AVAILABILITY OF DATA AND MATERIALS
All data generated or analyzed during this study are included in the published articles identified in this systematic review.
ACKNOWLEDGEMENTS
The authors extend their appreciation to the investigator support unit (ISU) of Prince Naif Health Research Center for the language editing service provided.

